
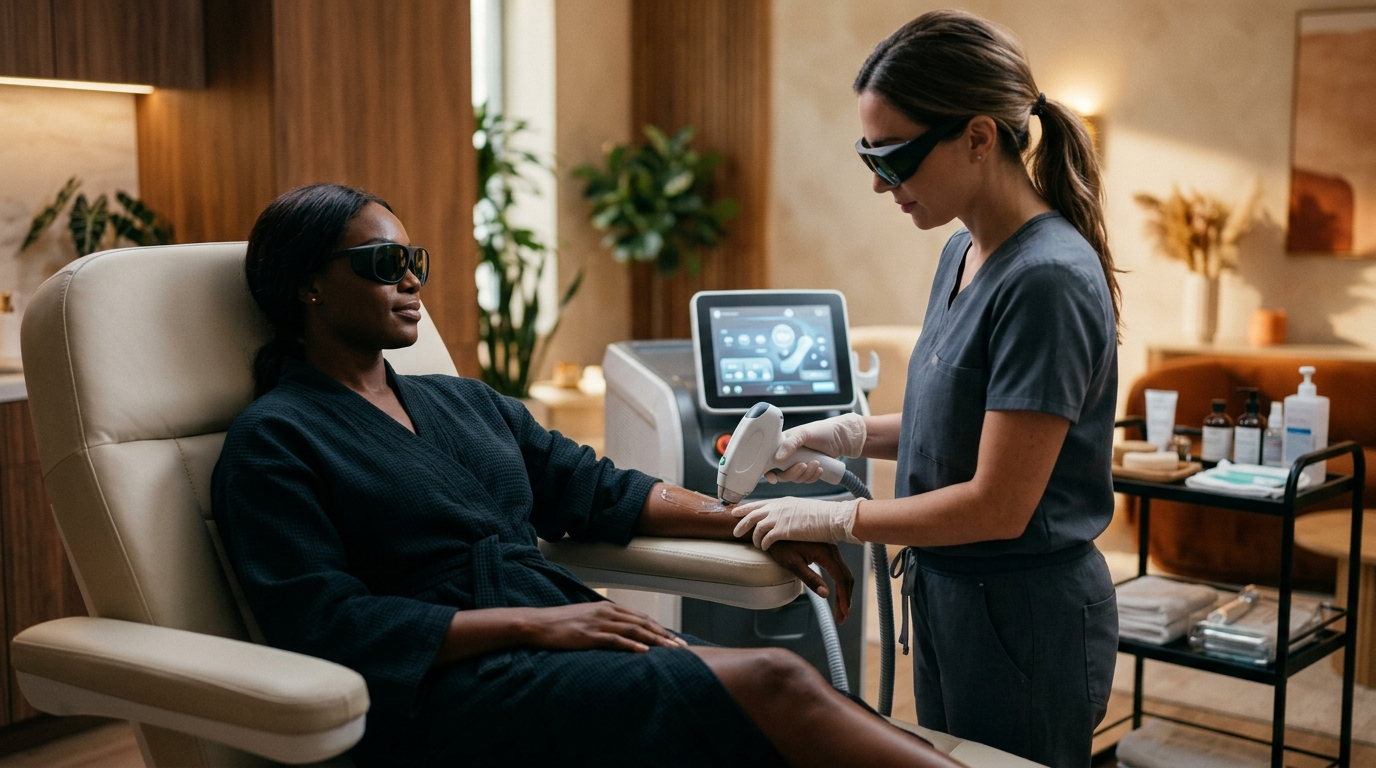
Clients with Fitzpatrick V and VI skin can be treated well. The outcomes, when done right, are genuinely excellent. The device has to match the skin. The protocol has to match the device. When those two things line up, dark skin responds beautifully to laser hair removal. When they don’t, you’re looking at burns, post-inflammatory hyperpigmentation, or depigmentation. All of that is preventable. All of it is avoidable. The real risk isn’t the patient. It’s a clinic running equipment that was never built for deeper melanin concentrations.
Why Does Skin Type Change the Entire Game?
Selective photothermolysis is the physics behind laser hair removal. The laser targets melanin inside the hair follicle. It heats the follicle enough to shut down regrowth. Surrounding tissue stays unaffected — that’s the intended outcome. In lighter skin types, the contrast between follicular melanin and epidermal melanin is wide. The laser has a clean target. In Fitzpatrick V and VI skin, that contrast narrows sharply. The epidermis carries considerably more melanin. A poorly selected wavelength absorbs in the skin before reaching the follicle. The surface takes the heat instead of the follicle. That’s where burns start.
Which Wavelength Is Actually Right for This Skin Type?
Device selection here is a clinical call, not a marketing one. Three wavelengths dominate the conversation around darker skin treatment.
- Nd:YAG 1064 nm — This is the established standard for Fitzpatrick V–VI. The longer wavelength penetrates deep into the dermis. Epidermal melanin absorbs very little of it. The follicle is the target, and the surface stays protected. Any clinic serious about treating darker skin types needs an Nd:YAG platform. That’s the baseline.
- Diode 810 nm — This works in the mid-range. Longer pulse durations and contact cooling improve the safety margin. Some diode platforms perform acceptably on Type V–VI skin. The margin for error is smaller than Nd:YAG. Device specifications vary widely in this category.
- Alexandrite 755 nm and IPL — These two are not appropriate for Type V–VI skin. Shorter wavelengths carry a real absorption risk in melanin-dense epidermis. The clinical literature on adverse events with these modalities on darker skin tones is well-established. This isn’t a grey area.
What Protocol Changes Actually Protect the Patient?
The right wavelength is the starting point. Protocol calibration closes the gap between a good result and a complication.
▸ Pulse duration: Longer pulses slow down heat dissipation. That reduces epidermal thermal damage risk significantly. For dark skin, longer pulses are standard — not optional.
▸ Fluence: Start conservative. Titrate upward across sessions. Aggressive fluence on a first treatment is a liability, not a time-saver.
▸ Repetition rate: Slower rates prevent cumulative thermal buildup in the epidermis. Faster isn’t better here.
▸ Cooling: Integrated contact cooling or cryogen spray is not optional on Type V–VI skin. It keeps the epidermal surface from absorbing heat that belongs deeper.
▸ Test patches: Every new patient. Every new device. This is baseline clinical practice, not a courtesy.
Reading skin response in real time matters. Operators who adjust mid-session based on what they observe consistently get better outcomes. Running a preset and walking away isn’t enough for this population.
What Should the Device Spec Sheet Actually Answer?
When evaluating a platform intended for darker skin types, the spec sheet has to answer specific questions before any purchase decision makes sense.
→ Does the system include a 1064 nm Nd:YAG handpiece? Is it standard or a costly add-on?
→ What are the maximum pulse duration settings? Do they reach ranges recommended for Type V–VI skin?
→ What integrated cooling technology is built directly into the handpiece?
→ Does the device offer variable spot sizes? Smaller sizes at lower fluence help with initial test patches.
→ What clinical data or regulatory clearance supports use on darker skin types specifically?
Platforms that market themselves as suitable for all skin types without the wavelength to back it up are common. Ask for the clinical data. Not the brochure.
Is There a Real Business Case for Serving This Demographic?
The patient population seeking laser hair removal is not majority Fitzpatrick I–III. Darker skin types represent a large underserved segment across most markets. In major Canadian and US cities, many clinics still decline Fitzpatrick V–VI patients outright. Either the device can’t handle it, or the staff isn’t trained on adjusted protocols. Both are fixable. Clinics that invest in Nd:YAG technology and proper operator training open access to a demographic with historically very few options. Referral patterns in this group tend to be strong. When a clinic treats everyone safely, word gets around. That reputation compounds.
Speak to Incredible Laser’s Team for your clinic needs.


